
Metabolic dysfunction-associated steatotic liver disease (MASLD) is the most prevalent chronic liver disease worldwide and involves interacting metabolic, oxidative, inflammatory, and fibrogenic processes that drive hepatocellular injury and disease progression [1–6]. This complex pathophysiology has stimulated interest in multi-target approaches, including phytotherapeutic and nutraceutical interventions as adjuncts to conventional management. Several compounds used in such interventions, including curcumin, silymarin, and dietary polyphenols, have been investigated in clinical studies and systematic reviews [7–10].
A key challenge is the interpretation of biomarkers used to characterize treatment-associated responses. Interleukin-11 (IL-11), historically associated with tissue protection and regeneration, has sometimes been interpreted as a potentially favorable biomarker, with increased circulating concentrations attributed to regenerative activity. However, recent species-matched experimental studies and emerging human evidence challenge this interpretation by implicating hepatic IL-11 signaling in lipotoxic injury, oxidative stress, hepatic stellate-cell activation, and fibrogenesis.
This Perspective examines this discrepancy without seeking to establish the efficacy of a specific formulation. We ask whether attenuation of processes associated with hepatic injury is accompanied by reduced hepatic IL-11 induction and whether such changes are reflected in circulating IL-11 concentrations. We therefore propose a conceptual framework of competing, not necessarily mutually exclusive, hypotheses for treatment-associated IL-11 dynamics.
The direction and temporal pattern of changes in circulating IL-11 are central to its interpretation as a potential response biomarker. If increased IL-11 is assumed to reflect regenerative activity, rising concentrations may be interpreted as favorable. Conversely, if hepatic IL-11 induction in MASLD occurs downstream of lipotoxic, oxidative, and transforming growth factor beta 1 (TGF-β1)-associated signaling, increased circulating IL-11 may be compatible with persistent hepatic stress and activation of pathways involved in hepatocellular injury and fibrogenesis. Thus, the same biomarker trajectory may support contrasting biological interpretations.
However, hepatic IL-11 signaling and circulating IL-11 concentrations are not interchangeable measures. Circulating IL-11 may reflect hepatic and extrahepatic production, release kinetics, distribution, clearance, and biological and analytical variability. An isolated change in circulating IL-11 therefore cannot be interpreted as a surrogate for hepatic pathway activity or used to guide clinical decisions. Its significance should be evaluated alongside markers of liver injury, oxidative and inflammatory activity, fibrosis-related measures, temporal response patterns, and biomarker variability. These relationships must be characterized before circulating IL-11 can be meaningfully evaluated as a response biomarker in prospective studies of metabolic liver disease.
This Perspective translates current evidence and uncertainties into four competing, but not necessarily mutually exclusive, hypotheses for treatment-associated IL-11 dynamics. We present an evidence-informed framework linking upstream processes to hepatic IL-11 induction and propose a prospective validation strategy incorporating predefined outcomes, explicit requirements for IL-11 measurement, and a staged study design. The aim is not to assign a priori biological meaning to a specific IL-11 trajectory, but to establish testable criteria for evaluating alternative interpretations prospectively.
This Perspective integrates selected experimental and clinical evidence with a methodological analysis of IL-11 biomarker interpretation. Targeted literature searches were conducted through 29 September 2026 using PubMed and relevant publisher sources. Search terms combined IL-11/IL11 with MASLD, nonalcoholic fatty liver disease (NAFLD), nonalcoholic steatohepatitis (NASH), circulating, serum, biomarker, and component-specific liver-disease terms, supplemented by citation tracing. Sources were selected for their relevance to hepatic IL-11 biology, circulating IL-11 measurement, and the mechanisms addressed in the proposed framework.
Throughout the appraisal, direct experimental findings are distinguished from extrapolations and assumptions regarding dose, exposure, and clinical applicability. The Scale for the Assessment of Narrative Review Articles (SANRA) domains informed the structure and reporting of the narrative appraisal [11].
The twelve components of the patent-pending encapsulated formulation developed by four of the authors (I.M., V.C., I.B., and N.R.) were mapped onto the upstream biological nodes defined in the proposed mechanistic framework. The formulation was examined because it was used in the clinical observation that prompted the present hypothesis, rather than as an independently selected representative formulation. For each component, evidence was appraised according to study design, mechanistic directness, studied exposure, and applicability to the formulation. Evidence sources included human randomized trials and meta-analyses, human non-randomized studies, animal experiments, in vitro studies, and mechanistic evidence. Constituent-to-node relationships were classified as direct, indirect, supported at the compound-class level, or extrapolated from non-hepatic experimental systems. This author-defined approach was used as an evidence-mapping framework and not as a validated certainty-of-evidence grading system.
The historical view of IL-11 as a hepatoprotective cytokine has been challenged by studies using species-matched reagents and genetic or pharmacological loss-of-function approaches. In the experimental systems examined, these studies support a contrasting role for endogenous IL-11 signaling in liver injury [12–14].
Early interpretations of IL-11 as a tissue-protective and regenerative cytokine arose from several observations. IL-11 was initially characterized for its hematopoietic effects, and recombinant human IL-11 (rhIL-11) was subsequently developed as a thrombopoietic agent. In addition, IL-11 signals through a gp130-containing receptor complex, linking it to pathways involved in hepatic acute-phase responses and regeneration. Finally, IL-11 expression is strongly induced in experimental liver injury, while rhIL-11 administration was reported to reduce injury in rodents. Together, these findings supported the hypothesis that IL-11 represented an endogenous protective response that could be therapeutically enhanced.
This interpretation, however, requires reconsideration. Increased expression of a mediator during tissue injury does not establish a protective function and may also reflect injury progression or maladaptive repair. Moreover, the apparent protective effects of exogenous rhIL-11 in mice did not demonstrate that endogenous, species-matched IL-11 exerted the same biological effects.
A major change in the interpretation of IL-11 biology came from recognizing important differences between human and mouse IL-11. In mouse hepatocytes, species-matched mouse IL-11 activated injury-related ERK and JNK signaling and caspase-3 cleavage, whereas recombinant human IL-11 (rhIL-11) did not produce the same effects [12]. Similar findings were observed in experimental acetaminophen-induced liver injury.
However, earlier experimental studies reported findings consistent with hepatoprotective or regenerative effects of IL-11. Nishina et al. showed that oxidative stress induced hepatocyte IL-11 production and that IL-11 promoted STAT3-dependent compensatory proliferation in adjacent hepatocytes after acute liver injury. IL-11 receptor agonism also reduced acetaminophen-induced injury, whereas IL-11Rα deficiency aggravated it [15]. Other mouse studies reported protective effects of rhIL-11 in hepatic ischemia–reperfusion injury, including reduced hepatocellular injury, apoptosis, and inflammatory signaling [16,17].
The species-mismatch hypothesis provides a plausible explanation for some of these apparently conflicting findings, because human IL-11 and endogenous mouse IL-11 may not produce equivalent signaling responses in mouse hepatocytes [12]. However, species mismatch may not fully explain all discordant observations, particularly studies involving receptor agonism, genetic IL-11Rα deficiency, or different injury models. The available evidence therefore supports a context- and model-dependent interpretation rather than a universally protective or universally detrimental role for IL-11.
Loss-of-function studies provide further evidence against a regenerative role for endogenous hepatic IL-11 signaling. In acetaminophen-induced liver injury, hepatocyte-specific deletion of the IL-11 receptor alpha gene (Il11ra) or germline deletion of the IL-11 gene (Il11) protected mice and reduced JNK and ERK activation [12]. Pharmacological inhibition of IL-11 signaling also reduced liver injury and improved survival, even when treatment was delayed after acetaminophen overdose. Importantly, IL-11 inhibition increased markers of hepatocyte proliferation, suggesting enhanced rather than impaired regeneration [12].
Experimental models of metabolic liver disease support a similar interpretation. Inhibition of IL-11 signaling reduced hepatocyte death, inflammation, steatosis, and fibrosis in mouse models of NASH [13], while hepatocyte-specific IL-11 signaling has been implicated in lipotoxicity and progression from NAFLD to NASH [14]. Mechanistically, injured hepatocytes can release IL-11, which may amplify cellular injury through NADPH oxidase 4 (NOX4)-dependent oxidative stress, mitochondrial dysfunction, and JNK activation [12–14].
Together, these findings support a role for hepatic IL-11 signaling in hepatocellular injury and maladaptive repair in the experimental systems studied [12–14,18–20]. However, they do not establish circulating IL-11 as a quantitative surrogate for intrahepatic IL-11 activity.
Human evidence linking circulating IL-11 to MASLD severity remains limited and predominantly observational. In a cross-sectional study of 375 outpatients with MASLD, liver stiffness was significantly higher in individuals with detectable serum IL-11 than in those with undetectable levels. Controlled attenuation parameter (CAP) values did not differ significantly between groups, while detectable serum IL-11 was independently associated with the study-defined advanced-fibrosis category [21].
Three limitations are particularly relevant. First, the cross-sectional design demonstrates an association between detectable circulating IL-11 and non-invasive measures of fibrosis severity but cannot establish whether changes in IL-11 reflect changes in fibrosis or hepatic IL-11 signaling over time.
Second, the reported difference was primarily between detectable and undetectable IL-11 rather than across a continuous concentration range. The large proportion of samples below the assay detection threshold raises important questions about assay sensitivity and the reliability of longitudinal measurements.
Third, the association was primarily related to fibrosis rather than steatosis. These findings therefore provide limited evidence for predicting short-term changes in circulating IL-11 during interventions targeting metabolic dysfunction or steatosis, particularly in patients without advanced fibrosis.
Although recent species-matched loss-of-function studies support a detrimental role for endogenous hepatic IL-11 signaling, earlier genetic, receptor-agonist, and ischemia–reperfusion studies reported protective or regenerative effects. These discrepancies may partly reflect species mismatch, experimental context, injury model, ligand or agonist used, dose, and timing, but they remain incompletely resolved. Against this background, four uncertainties are particularly relevant to the framework developed below.
First, the quantitative relationship between intrahepatic IL-11 activity and circulating IL-11 concentrations has not been established. Circulating IL-11 therefore cannot currently be considered a validated surrogate for hepatic IL-11 pathway activity.
Second, IL-11 is produced by multiple extrahepatic tissues and cell types. Circulating IL-11 is therefore not liver-specific, and treatment-associated changes may reflect extrahepatic production, distribution, or clearance in addition to hepatic processes. This uncertainty provides the basis for the extrahepatic/off-axis hypothesis developed later in this framework.
Third, IL-11 biology is tissue-, disease-, and context-dependent [18–20]. The present framework is therefore restricted to evidence relevant to metabolic and experimental liver disease and should not be generalized to other physiological or pathological settings. Fourth, our targeted appraisal did not identify prospective MASLD intervention studies examining whether individual changes in circulating IL-11 parallel changes in hepatic injury, oxidative stress, or fibrogenic activity. The expected trajectory of circulating IL-11 during an effective intervention therefore remains a conditional, mechanism-dependent prediction rather than an established treatment-response pattern. Given the narrative nature of the search, this finding should not be interpreted as evidence that such studies definitively do not exist.
For the purposes of this Perspective, IL-11 nutrigenomodulation refers to the hypothesis that dietary bioactive compounds may influence biological processes involved in hepatic IL-11 induction or signaling. Based on the evidence reviewed above, this concept should not assume that a favorable intervention increases IL-11. Instead, we consider whether bioactive compounds may influence upstream processes associated with hepatic IL-11 activity, including lipotoxic and mitochondrial stress, oxidative stress, TGF-β1/SMAD signaling in hepatic stellate cells, inflammatory signaling, and gut-derived inflammatory stimuli.
Within this framework, attenuation of relevant upstream drivers may reduce hepatic IL-11 induction or signaling when these pathways are active in the biological context studied. However, changes in circulating IL-11 cannot be predicted directly from hepatic signaling because they may also depend on extrahepatic production, release, distribution, and clearance. Circulating IL-11 is therefore treated as a candidate downstream signal whose interpretation requires comparison with upstream biological changes and independent measures of hepatic injury and fibrogenic activity.
For analytical purposes, we define five interconnected biological nodes through which a multi-target intervention may influence processes related to hepatic IL-11 induction (Figure 1). These nodes differ in their proximity to IL-11 signaling and should not be interpreted as independent causal pathways. Together, they provide a framework encompassing metabolic, oxidative, profibrogenic, inflammatory, and gut-derived processes.
N1 — Lipotoxic and mitochondrial stress in hepatocytes. Free fatty-acid overload, mitochondrial dysfunction, and associated reactive oxygen species (ROS) generation can promote hepatocellular stress and IL-11 expression [5,6,14,18].
N2 — NOX4-derived oxidative stress. NOX4-dependent ROS generation is linked to IL-11 signaling and may form a feed-forward circuit in which oxidative stress promotes IL-11 induction and IL-11 signaling further enhances ROS generation [12,18]. N2 may therefore act both upstream and downstream of IL-11 signaling.
N3 — TGF-β1/SMAD signaling in hepatic stellate cells. TGF-β1 induces IL-11 expression in activated hepatic stellate cells, linking profibrogenic signaling to sustained IL-11 activity [13,18].
N4 — Inflammatory signaling and nuclear factor kappa B (NF-κB)-associated inflammatory tone . Proinflammatory mediators, including tumor necrosis factor alpha (TNF-α) and interleukin-1 beta (IL-1β), contribute to hepatic inflammation and interact with lipotoxic, oxidative, and profibrogenic pathways. Their relationship with IL-11 in this framework is considered primarily contextual and indirect [22].
N5 — Gut–liver axis and endotoxin exposure. Intestinal barrier dysfunction and translocation of microbial products, including lipopolysaccharide (LPS), can sustain hepatic inflammation and indirectly favor hepatic injury and IL-11 induction [3,4].
The proposed framework and the relationships among the five upstream nodes, hepatic IL-11 signaling, and downstream pathways are summarized in Figure 1.
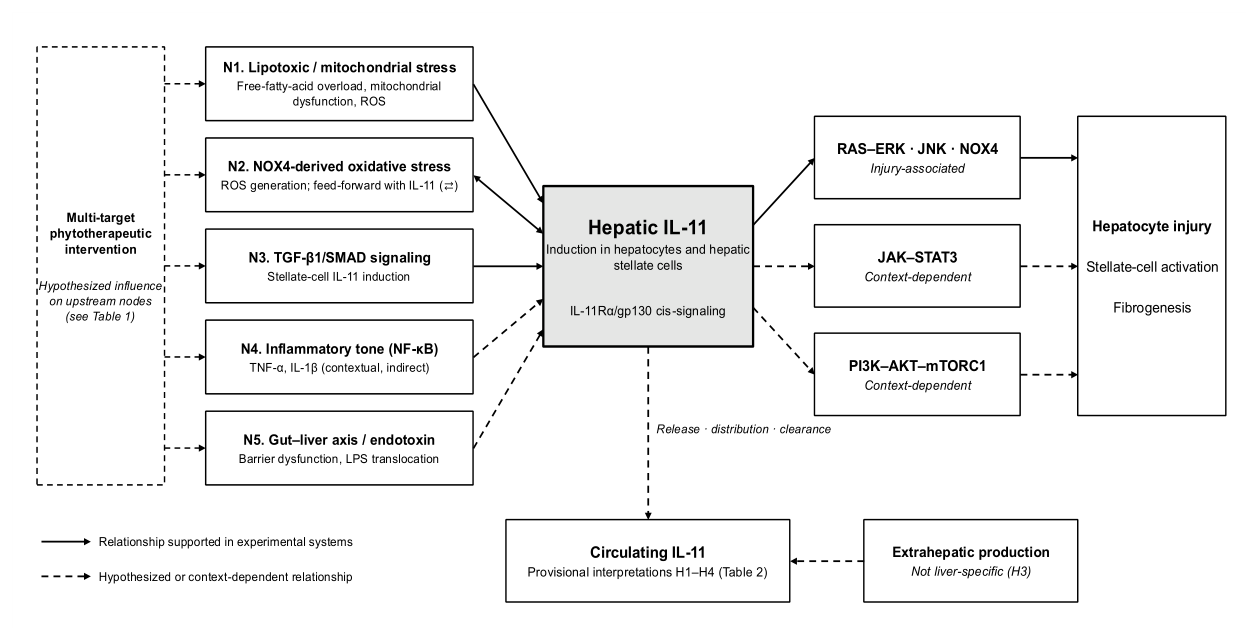
Note: Five interconnected nodes (N1–N5) represent metabolic, oxidative, profibrogenic, inflammatory, and gut-derived processes that may converge on IL-11 induction in hepatocytes and hepatic stellate cells. IL-11Rα/gp130 cis-signaling is shown because no evidence of IL-11 trans-signaling was identified in the hepatocyte and NASH models examined [14]. The bidirectional relationship between N2 and hepatic IL-11 represents oxidative feed-forward amplification involving NOX4-derived ROS. Circulating IL-11 may reflect hepatic release, distribution, and clearance, as well as extrahepatic production, and therefore cannot be considered a direct surrogate for hepatic IL-11 activity. H1–H4 denote the provisional interpretations summarized in Table 2. Solid arrows indicate relationships supported in experimental systems; dashed arrows indicate hypothesized or context-dependent relationships. Abbreviations: AKT, protein kinase B; ERK, extracellular signal-regulated kinase; gp130, glycoprotein 130; IL-1β, interleukin1 beta; IL-11, interleukin-11; IL-11Rα, interleukin-11 receptor alpha; JAK, Janus kinase; JNK, c-Jun N-terminal kinase; LPS, lipopolysaccharide; mTORC1, mechanistic target of rapamycin complex 1; NASH, nonalcoholic steatohepatitis; NF-κB, nuclear factor kappa B; NOX4, NADPH oxidase 4; PI3K, phosphoinositide 3-kinase; RAS, RAS family small GTPase; ROS, reactive oxygen species; SMAD, mothers against decapentaplegic homolog; STAT3, signal transducer and activator of transcription 3; TGF-β1, transforming growth factor beta 1; TNF-α, tumor necrosis factor alpha.
The twelve components of the patent-pending encapsulated formulation were mapped onto the upstream nodes defined above. Evidence varied substantially in study design, mechanistic directness, studied exposure, and applicability to the administered formulation. None of the available evidence establishes modulation of hepatic or circulating IL-11 by the complete formulation.
The formulation and complementary vegetable-based preparation were administered sequentially according to the protocol associated with the clinical observation described in Section 5. Full composition and administration details are provided in the Supplementary Material to ensure transparency and reproducibility.
Taxifolin, curcumin, and L-glutathione were specified as 98%, 95%, and 98%, respectively, whereas most botanical ingredients were characterized only by a 10:1 extract ratio. Because information on extraction solvents, standardization, and active-compound content was unavailable, equivalence with standardized preparations or isolated compounds evaluated in published studies cannot be assumed.
The complementary vegetable-based preparation contained carrot, aronia or blueberries, dandelion root, chicory root, beetroot, dates, and ginger root. These components were mapped principally to N5 (dandelion and chicory), N1/N2 (anthocyanin-rich fruit and beetroot), and N4 (ginger). Evidence from randomized studies of ginger powder in NAFLD [23,24] cannot be directly extrapolated to fresh ginger root in this mixture, and aronia and blueberries were considered alternative rather than equivalent ingredients. Table 1 summarizes the constituent-to-node mapping together with the supporting evidence, studied exposures, and applicability to the administered formulation.
| Constituent (per capsule) | Node(s) | Evidence source | Measured outcome and node directness | Studied exposure | Applicability to formulation |
|---|---|---|---|---|---|
| Taxifolin 98%, 50 mg | N1, N2 | Animal studies | Reduced oxidative stress and apoptosis in experimental hepatic injury [25,26]; IL-11 relationship extrapolated | Animal dosing | Human exposure and node/IL-11 effects unestablished |
| Curcumin 95%, 45 mg | N1, N3, N4 | Human meta-analyses; in vitro studies | Liver biochemical outcomes [7]; TGF-β/SMAD effects in non-hepatic systems [27]; reduced ROS/steatosis with andrographolide in HepG2 cells [28]; node assignment partly indirect | ~500–1500 mg/day; often bioavailability-enhanced [7,29] | Dose, preparation, and exposure equivalence unestablished |
| Silybum marianum extract (10:1), 45 mg | N1, N4 | Human meta-analyses | Liver enzyme and metabolic outcomes in MASLD [7,8,30]; node assignment indirect | ~140–800 mg/day standardized silymarin [7,8,30] | Extract mass not equivalent to standardized silymarin content |
| Rhaponticum carthamoides extract (10:1), 40 mg | N1 | No direct study identified | Adaptogenic-class rationale; direct hepatic node or IL-11 evidence not identified | No supporting exposure identified | Applicability unestablished |
| Zingiber officinale extract (10:1), 40 mg | N4 | Human randomized trials | Liver, inflammatory, and metabolic outcomes in NAFLD [23,24]; no IL-11 outcome | Ginger powder, 2 g/day for 12 weeks [23] | Powder exposure does not establish equivalence with this extract or regimen |
| Aronia melanocarpa extract (10:1), 35 mg | N1, N2 | Human evidence, compound-class level | Polyphenol intervention evidence [9]; compound-class extrapolation without aronia-specific IL-11 evidence | Varied polyphenol preparations | Species, extract, and exposure equivalence unestablished |
| Cichorium intybus extract (10:1), 35 mg | N5 | Mechanistic/compound-class evidence | Inulin-type fructan gut–liver rationale [3,4]; extract-specific effect unestablished | Gram-scale prebiotic exposure | Fructan content and corresponding exposure unknown |
| Andrographis paniculata extract (10:1), 35 mg | N1, N4 | In vitro study | Andrographolide with curcumin reduced steatosis and ROS in HepG2 cells [28]; node assignment indirect | Cell-culture exposure | Andrographolide content and clinical exposure unknown |
| Glycyrrhiza glabra extract (10:1), 35 mg | N4 | No direct study identified | Anti-inflammatory class rationale; direct node or IL-11 evidence not established | No supporting exposure identified | Active-compound content and exposure unestablished |
| Juglans regia extract (10:1), 30 mg | N1 | No direct study identified | Phenolic-profile rationale; direct node or IL-11 evidence not established | No supporting exposure identified | Applicability unestablished |
| Phoenix dactylifera extract (10:1), 30 mg | — | No node-specific evidence | Nutritive component; no specific mechanistic claim | Not applicable | No IL-11 inference |
| L-glutathione 98%, 55 mg | N1, N2 | Human uncontrolled pilot | Reduced ALT in NAFLD [31]; variable oral bioavailability/systemic effects [32,33]; node assignment indirect | 300 mg/day [31] | Dose equivalence and node/IL-11 effects unestablished |
Abbreviations: ALT, alanine aminotransferase; IL-11, interleukin-11; MASLD, metabolic dysfunction-associated steatotic liver disease; NAFLD, nonalcoholic fatty liver disease; ROS, reactive oxygen species; TGF-β, transforming growth factor beta.
Three main findings emerge from the evidence mapping. First, clinical evidence is concentrated around curcumin and silymarin, supported by meta-analyses in MASLD [7,8], and ginger, evaluated in randomized NAFLD trials [23,24]. These studies report biochemical, inflammatory, or metabolic outcomes but do not demonstrate IL-11 modulation. Evidence for the remaining components is predominantly indirect, compound-class, in vitro, animal, or inferential.
Second, the targeted appraisal identified no direct evidence that the complete formulation modulates hepatic or circulating IL-11 and no human clinical evidence directly demonstrating modulation of the TGF-β1/SMAD–IL-11 pathway represented by N3. Such an effect would therefore require two unverified steps: that the administered components modify the proposed upstream nodes at clinically relevant exposures, and that these changes produce a measurable alteration in hepatic or circulating IL-11.
Third, the complementary vegetable-based preparation principally maps to the gut–liver axis (N5) and to oxidative and metabolic processes (N1/N2). Because it was introduced after initiation of the encapsulated formulation, its independent contribution cannot be determined from the sequential regimen. Future studies should therefore separate the individual and combined effects of the two intervention components.
The framework developed above generates four competing, but not necessarily mutually exclusive, explanations for intervention-associated changes in circulating IL-11. Their consistency with observed data can be evaluated prospectively by considering IL-11 direction and temporal pattern, covariation with hepatic and oxidative-stress biomarkers, treatment exposure and withdrawal, and reproducibility across repeated observations.
Two outcomes should be considered separately: the randomized treatment effect on circulating IL-11 and the within-person association between IL-11 and prespecified biochemical markers. Change-score associations require cautious interpretation because correlated measurement error, regression to the mean, and common temporal trends may distort apparent relationships (Supplementary Methods S5).
The intervention attenuates one or more upstream drivers of hepatic IL-11 induction, particularly the lipotoxic, oxidative, inflammatory, and gut-derived processes represented by N1, N2, N4, and N5. If this reduces hepatic IL-11 induction, circulating IL-11 would be expected to decline when hepatic production contributes substantially to circulating concentrations and extrahepatic production and clearance remain sufficiently stable.
Based on the historical regenerative interpretation of IL-11, an alternative hypothesis is that a favorable intervention produces a transient increase in circulating IL-11 during an adaptive or regenerative response. Under this model, IL-11 would rise despite biochemical improvement. Such a pattern would not, however, establish regeneration, because persistent profibrogenic signaling, altered clearance, extrahepatic production, and analytical effects remain alternative explanations.
Changes in circulating IL-11 may arise partly from extrahepatic sources and therefore correlate weakly with hepatic IL-11 activity. Alternatively, intervention components may influence IL-11 or related signaling pathways outside the upstream nodes N1–N5. An extrahepatic interpretation requires positive source-related evidence rather than merely the absence of correlation with hepatic markers.
Exploratory assessment could incorporate prespecified systemic inflammatory measures or source-related measurements. Soluble IL11Rα may be investigated, but its concentration alone neither localizes IL-11 production nor establishes functional trans-signaling, which was not supported in the hepatocyte and NASH models examined in reference [14].
Observed changes in circulating IL-11 may reflect assay imprecision, preanalytical variability, biological fluctuation, assay interference, or batch effects rather than an intervention-related biological response. This possibility is particularly relevant because reported circulating IL-11 concentrations vary across studies and assay platforms, and some measurements may fall near or below detection or quantification limits.
In one exploratory adult series, median serum IL-11 concentrations ranged from approximately 62 to 95 pg/mL, with 6.8% of measurements below the assay detection limit [34]. In a large MASLD cohort, the principal analyzable comparison was between detectable and undetectable IL-11 [21]. These observations do not define analytical error or a reference interval for MASLD but emphasize the need for caution when interpreting small absolute changes. Values in the 18–28 pg/mL range therefore require platform-specific evaluation of assay precision, detection and quantification limits, sample handling, storage, freeze–thaw exposure, and within-subject variability.
Table 2 summarizes the directional, temporal, and reproducibility patterns that would be consistent with each hypothesis; none of these patterns independently establishes mechanism.
| Observation | H1: Upstream suppression | H2: Adaptive rise | H3: Extrahepatic/off-axis | H4: Null/analytical |
|---|---|---|---|---|
| Direction of IL-11 change | Decrease, conditional on hepatic contribution and stable clearance | Transient increase; regeneration not established | Either direction; source requires separate assessment | Either direction; random or systematic analytical effects |
| Within-person biomarker association | Possible positive association as IL-11 and injury/oxidative markers decrease | Possible negative association during biochemical improvement | Weak hepatic association may occur; source-related evidence required | No stable association with random error; interference may mimic one |
| Temporal relationship | Decline with or after upstream-marker improvement | Rise before or during improvement; biological meaning unresolved | May track an extrahepatic source or off-axis effect | Random fluctuation or systematic batch/exposure-related pattern |
| Repeated exposure/withdrawal | Reproducible pattern supports exposure association | Reproducible rise supports exposure association, not regenerative benefit | Reproducibility does not localize the source | Inconsistency supports noise; reproducibility does not exclude interference |
| Longer-term fibrosis measures | Lower IL-11 with stable/improved measures is compatible with H1 but not confirmatory | Absence of worsening does not establish regeneration | Absent association does not establish an extrahepatic source | No relationship or potentially misleading analytical association |
| IL-6/systemic context | Broader inflammatory improvement may accompany IL-11 decline | Divergence between IL-11 and IL-6 is nonspecific | Independent source/context evidence is required | Analytical effects require independent exclusion |
Abbreviations: IL-6, interleukin-6; IL-11, interleukin-11; H1, upstream-suppression hypothesis; H2, adaptive-rise hypothesis; H3, extrahepatic or off-axis hypothesis; H4, null/analytical hypothesis.
No single observation can distinguish these hypotheses. Direction, biomarker covariation, temporal ordering, and repeated exposure/withdrawal can test consistency with H1 and H2 but cannot establish mechanism or regenerative benefit. H3 requires positive source-related evidence, whereas H4 requires explicit assessment of analytical and preanalytical factors.
IL-11 trajectories also need not be monotonic; transient or biphasic responses are biologically plausible. Prospective testing should therefore prioritize serial measurements and prespecified temporal patterns rather than a single baseline-to-follow-up change. Reproducibility across exposure and withdrawal periods strengthens evidence for an exposure-associated signal but, without analytical controls and independent pathway assessment, does not establish its biological mechanism.
A single anonymized clinical observation is presented solely as the observation that prompted the present hypothesis and not as evidence of efficacy, causality, or biomarker validity.
A 68-year-old man with a dysmetabolic profile and documented hepatic steatosis showed decreases in alanine aminotransferase (ALT; 98 to 39 U/L), aspartate aminotransferase (AST; 94 to 36 U/L), gamma-glutamyl transferase (GGT; 214 to 42 U/L), C-reactive protein (CRP; 8.2 to 3.1 mg/L), and malondialdehyde (MDA; 4.2 to 0.8 µmol/L), while circulating interleukin-11 (IL-11) increased from 18.0 to 28.0 pg/mL.
The retrospective records did not permit reliable reconstruction of the sampling interval and corresponding treatment phases, the biological matrix or analytical platform used for IL-11 measurement, the method used for MDA determination, or the imaging method and grading system used to characterize steatosis. The marked MDA change should therefore be interpreted with particular caution. Additional limitations include the absence of repeated IL-11 measurements and incomplete information on medication stability and other potential confounders.
These limitations preclude quantitative interpretation of the biomarker trajectories or attribution of the observed changes to the intervention. Accordingly, this observation is not used as evidence for any of the competing hypotheses; it serves only to define the question addressed by the prospective validation strategy proposed in Section 6.
The proposed strategy comprises three sequential stages, with progression conditional on the reliability and reproducibility of the preceding findings (Figure 2). The initial objective is not to establish clinical efficacy, but to determine whether circulating IL-11 can be measured reliably, whether it shows a reproducible intervention-associated trajectory, and whether that trajectory is consistent with H1–H4. Biomarker patterns alone cannot establish mechanism.
Stage 1 — Analytical and biological variability. A non-interventional study in 25–30 adults with MASLD at increased fibrosis risk is proposed to characterize analytical and within-subject variability under stable conditions. Participants should undergo four standardized fasting assessments over six weeks. Age-adjusted Fibrosis-4 Index (FIB-4) thresholds (≥1.3, or ≥2.0 in individuals aged >65 years) should prompt vibration-controlled transient elastography (VCTE); liver stiffness ≥8 kPa indicates increased fibrosis risk rather than a confirmed histological stage [35]. Duplicate IL-11 measurements, preferably within a single analytical run and kit lot for each participant, with a subset assessed on a second platform, should be used to estimate analytical variability, within-subject biological variability, quantification frequency, and the 95% reference change value (RCV). The primary outcome is the within-subject variability of circulating IL-11 and the corresponding RCV. The proposed sample of 25–30 participants, each providing four repeated measurements, is intended as a precision-oriented feasibility sample for estimating within-subject variability and its uncertainty rather than for hypothesis testing; the resulting confidence intervals will determine whether the RCV is sufficiently precise for subsequent interventional use.
Progression gate 1. Interventional testing should proceed only if assay precision, quantification frequency, and the precision of the estimated RCV are adequate for longitudinal interpretation. The IL-11 change described in Section 5 should not be treated as an expected effect size. Inadequate measurement performance should prompt assay refinement or an alternative biomarker strategy before intervention testing.
Stage 2 — Exposure/withdrawal feasibility and randomized N-of-1 series. Conditional on Stage 1, dense sampling during initial exposure and withdrawal should characterize onset, offset, reversibility, and potential carry-over. If the observed kinetics permit, 8–12 randomized N-of-1 trials are proposed, each comprising at least three paired active-treatment/placebo periods. The encapsulated formulation should be compared with matched placebo without the vegetable-based preparation, allowing the capsule intervention to be evaluated separately. Period and washout durations should be determined from observed intervention-associated kinetics and carry-over. The N-of-1 series should follow the CONSORT extension for N-of-1 trials [36]. The primary outcome is the within-participant difference in circulating IL-11 between randomized active and placebo periods over a prespecified measurement window.
This design reduces interindividual variability and allows assessment of within-person reproducibility across repeated randomized exposures. Participant-level estimates may be combined hierarchically to examine consistency across the series. If IL-11 kinetics are too slow or carry-over cannot be adequately controlled, a randomized parallel-group design with serial sampling should replace the N-of-1 approach. Successful placebo matching, including color, odor, and taste, should be formally assessed.
Progression gate 2. Progression should require an analytically credible intervention-associated signal, interpretable prespecified biomarker trajectories, and acceptable safety and feasibility. These findings may support exposure association and mechanistic consistency but cannot independently establish biological mechanism or clinical benefit.
Stage 3 — Controlled parallel-group pilot. A 24-week randomized, placebo-controlled parallel-group pilot should compare the encapsulated formulation with matched placebo, both added to standard care. Concomitant treatment, dietary recommendations, physical activity, and relevant medications should be prospectively documented. VCTE should be performed at baseline and week 24, together with a validated assessment of hepatic steatosis where feasible. The primary mechanistic outcome is the between-group difference in the change in circulating IL-11 from baseline to week 24; feasibility outcomes include recruitment, retention, adherence, and completeness of longitudinal biomarker assessment.
Stage 3 is intended as a mechanistic feasibility pilot rather than a definitive efficacy trial. Its sample size should therefore be determined prospectively from the variance and intervention-associated IL-11 estimates obtained in Stages 1 and 2, together with predefined precision, recruitment, and retention criteria, rather than from an assumed clinical effect size.
The complementary vegetable-based preparation should be evaluated separately or within a design capable of distinguishing the effects of the encapsulated formulation, the vegetable-based preparation, and their combination.
The complete outcome panel, sampling schedule, IL-11 analytical specifications, safety monitoring, and statistical analysis plan are provided in the Supplementary Material.
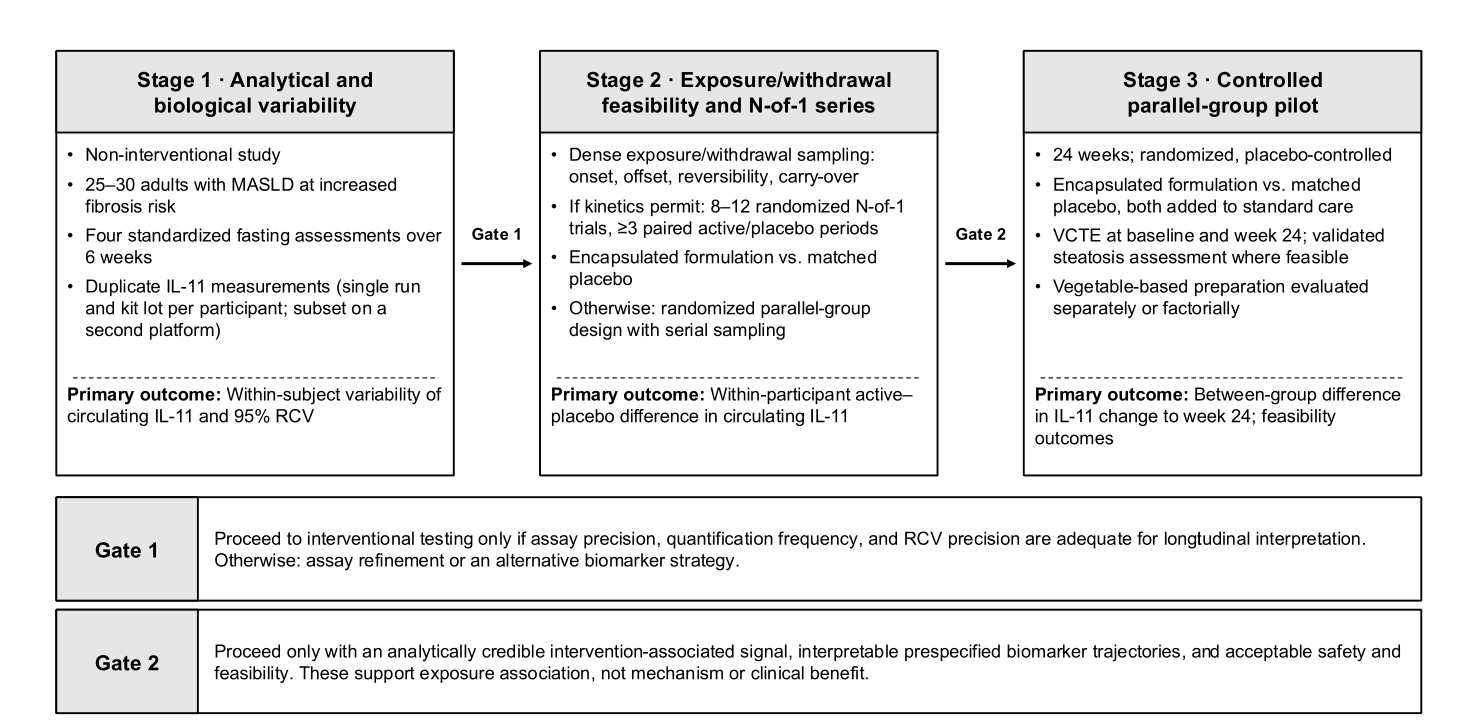
Note: Stage 1 characterizes analytical and within-subject biological variability in circulating IL-11 and establishes assay detectability and the reference change value (RCV). Conditional on adequate measurement performance, Stage 2 evaluates intervention-associated kinetics, reversibility, and carry-over through exposure/withdrawal sampling and, where appropriate, randomized N-of-1 trials. Stage 3 is a 24-week randomized, placebo-controlled mechanistic feasibility pilot. Progression between stages requires an analytically credible and reproducible signal together with acceptable safety and feasibility. Biomarker trajectories may support exposure association and mechanistic consistency but do not independently establish mechanism or clinical efficacy. Abbreviations: IL-11, interleukin-11; RCV, reference change value.
The proposed framework is intended to prevent circulating IL-11 trajectories from being interpreted independently of their biological, analytical, and temporal context. Four principles should guide future studies.
This staged strategy is designed to establish whether an intervention-associated IL-11 signal is reproducible while distinguishing upstream-suppression, adaptive-rise, extrahepatic/off-axis, and analytical explanations before larger efficacy studies are undertaken.
The principal implication of this reappraisal is a change in how circulating IL-11 trajectories should be interpreted during interventions targeting metabolic liver injury. Current evidence does not support interpreting an increase in circulating IL-11 as inherently favorable or regenerative. Its biological significance should instead be assessed in relation to upstream processes, concurrent hepatic and oxidative-stress markers, temporal patterns, and analytical reliability.
Under the upstream-suppression hypothesis (H1), attenuation of lipotoxic, oxidative, and inflammatory stress would be expected to reduce hepatic injury. A corresponding decline in circulating IL-11, however, remains conditional on hepatic contribution and sufficiently stable extrahepatic production and clearance. Conversely, improvement in ALT, GGT, MDA, or inflammatory markers accompanied by increased IL-11 represents a discordant pattern requiring further investigation rather than evidence of regeneration.
The evidence mapping provides stronger clinical support for selected components, particularly curcumin, silymarin, and ginger, but does not establish that the complete formulation modulates hepatic IL-11 or its proposed upstream determinants at the administered exposures. The framework therefore does not predict that the formulation necessarily reduces circulating IL-11. Rather, it defines the biological conditions under which such a reduction would be consistent with H1 and the evidence required to evaluate this prediction.
This reappraisal does not evaluate the clinical efficacy of multi-target interventions in MASLD. The rationale for such approaches derives from the multifactorial nature of the disease, involving interacting metabolic, lipotoxic, oxidative, inflammatory, fibrogenic, and gut–liver processes [2,3,9,10,37]. Whether a specific combination produces clinically meaningful benefit requires direct evaluation.
The central methodological issue is not whether multi-target interventions are intrinsically beneficial, but whether the proposed biological relationships are explicit, evidence-based, and testable. A biomarker cannot validate an intervention when the expected direction and biological meaning of its change have not themselves been established.
The evidence matrix makes these inferential steps explicit. Evidence that a component improves selected outcomes in MASLD does not establish modulation of its assigned upstream node, and evidence of an upstream effect does not establish downstream modulation of IL-11. Likewise, evidence derived from compound-class, non-hepatic, in vitro, or theoretical sources should not acquire greater certainty simply because a component is included in a multi-ingredient formulation. The same principle applies to interactions and synergy: biological plausibility alone does not demonstrate effects beyond those of the individual components.
This work is conceptual and methodological and generates no new experimental evidence. Its conclusions therefore depend on the literature identified, the validity of the proposed biological relationships, and their prospective testability.
First, the evidence mapping was based on a targeted narrative appraisal rather than a systematic review with duplicate screening and independent risk-of-bias assessment. Individual node assignments may therefore change as additional evidence emerges. Moreover, evidence of a clinical or biochemical effect does not establish modulation of the assigned node or of IL-11 itself. Much of the experimental evidence central to the revised interpretation of hepatic IL-11 derives from overlapping research groups [12–14], emphasizing the importance of independent replication.
Second, the relationship between circulating and intrahepatic IL-11 remains insufficiently characterized. Circulating concentrations cannot currently be considered a validated surrogate for hepatic production or cell-specific IL-11 pathway activity. Human evidence in MASLD remains limited, with the principal circulating IL-11 evidence derived from cross-sectional data [21], while mechanistic support includes human hepatocyte and liver-tissue studies alongside animal models [14]. The proposed reframing should therefore be regarded as a testable interpretation rather than an established model of human MASLD.
Third, the clinical observation in Section 5 is inherently hypothesis-generating. Its single-patient, uncontrolled, sequential design, concurrent supportive management, limited temporal sampling, and non-replicated IL-11 measurements preclude causal interpretation of either the biochemical changes or the IL-11 trajectory.
Fourth, analytical uncertainty remains substantial. Assay sensitivity, sample handling and storage, batch effects, and within-subject biological variability may influence apparent longitudinal changes in circulating IL-11. Their magnitude and clinical relevance remain insufficiently characterized, which is why the proposed validation strategy begins with analytical and biological variability rather than intervention testing.
Finally, IL-11 biology is tissue-, disease-, and context-dependent [18–20]. The framework and interpretive rules proposed here are restricted to metabolic liver disease and should not be extrapolated to other organs, diseases, or therapeutic settings without independent evidence.
Future research should first establish the analytical reliability of circulating IL-11 at concentrations relevant to longitudinal studies. Comparative assay studies should define precision, detection and quantification limits, preanalytical stability, and within-subject biological variability.
Experimental studies should then examine the effects of individual components and the complete formulation on IL11 transcription, IL-11 protein production, and downstream signaling in human hepatocytes and hepatic stellate cells. These studies should distinguish modulation of upstream oxidative, inflammatory, and TGF-β-related pathways from direct effects on IL-11 signaling.
Paired hepatic and circulating measurements would help determine whether circulating IL-11 reflects intrahepatic IL-11 activity. Where liver tissue is obtained for clinical indications, tissue expression, protein levels, and downstream signaling could be compared with circulating concentrations.
Prospective intervention studies should assess the reproducibility, timing, and biomarker relationships of IL-11 trajectories and their consistency with H1–H4. The staged strategy proposed in Section 6 provides a framework for this evaluation before larger efficacy trials.
Finally, the complementary vegetable-based preparation should be evaluated independently rather than inferred from sequential administration. Factorial or other interaction-capable designs could distinguish the effects of the encapsulated formulation, the vegetable-based preparation, and their combination, including any evidence of interaction or synergy.
Current evidence challenges the historical interpretation of IL-11 as an inherently protective or regenerative cytokine in metabolic liver disease. Experimental studies implicate hepatic IL-11 signaling in lipotoxic and oxidative stress, fibrogenic signaling, hepatocyte injury, and hepatic stellate-cell activation, while human evidence suggests an association between circulating IL-11 and fibrosis severity.
Within the upstream-suppression hypothesis, attenuation of these processes may be accompanied by a decline in circulating IL-11, provided that hepatic production contributes substantially and extrahepatic production and clearance remain sufficiently stable. This remains a testable hypothesis rather than an established treatment-response pattern. Adaptive-rise, extrahepatic/off-axis, and analytical explanations therefore require prospective evaluation through serial measurements, temporal assessment, within-subject replication, and appropriate analytical controls.
Before circulating IL-11 can be used as a response biomarker, its analytical and biological variability and the magnitude of change that can be reliably detected must be established. Until then, an intervention-associated increase in circulating IL-11 should be considered an unexplained finding rather than evidence of therapeutic benefit. In metabolic liver disease, the biological meaning of an IL-11 trajectory must be demonstrated rather than assumed.
A patent application related to the encapsulated composition, vegetable-based preparation, and administration protocol described in this manuscript has been filed with the State Agency on Intellectual Property of the Republic of Moldova (AGEPI). The application is pending, and no patent has been granted.
I.M., V.C., I.B., and N.R. are inventors and owners of a patent application relating to the encapsulated phytotherapeutic composition, the complementary vegetable-based formula, and the administration protocol discussed in this manuscript. The application has been filed with the State Agency on Intellectual Property of the Republic of Moldova (AGEPI) and is currently pending; no patent has yet been granted. The inventors report no commercial role related to the formulation. D.M.C., C.O.D., M.C.V., V.G.D., C.D.M., and G.P.G. declare no competing interests. This work received no external funding.
Generative artificial intelligence was used solely to assist with language editing, grammatical correction, and improvement of clarity and readability. It was not used to generate research data, perform analyses, select or interpret evidence, or formulate the scientific conclusions of the manuscript. All AI-assisted text was critically reviewed and revised by the authors, who take full responsibility for the final content.
All figures and tables were created by the authors specifically for this manuscript and are original. No copyrighted figures, images, or tables from other sources were reproduced or adapted.
Author contributions. Conceptualization, I.M., D.M.C. and C.O.D.; methodology, I.M., V.C., I.B., N.R. and C.O.D.; validation, C.O.D., D.M.C. and M.C.V.; formal analysis, C.O.D., I.M. and M.C.V.; investigation, I.M., V.C., I.B. and N.R.; resources, I.M., V.C., I.B. and N.R.; data curation, I.M., V.C., I.B., N.R. and C.O.D.; writing—original draft preparation, I.M., V.C., I.B., N.R. and C.O.D.; writing—review and editing, C.O.D., D.M.C., M.C.V., V.-G.D., C.D.M. and G.P.G.; visualization, C.O.D. and M.C.V.; supervision, I.M., D.M.C. and G.P.G.; project administration, I.M., D.M.C. and C.O.D. All authors have read and agreed to the published version of the manuscript. I.M. and D.M.C. contributed equally to this work and share first authorship.
This article reports no new experimental research involving human participants. The single anonymized clinical observation described in Section 5 arose from routine individualized clinical practice. The use of anonymized clinical and laboratory data from this observation for scientific purposes was approved by the Ethics Committee of Clinical Hospital CF2 Bucharest, Bucharest, Romania (approval no. 3/13.10.2025). The individual provided written informed consent for the publication of the anonymized clinical and laboratory data presented in this article.
Written informed consent was obtained from the patient for the publication of the anonymized clinical and laboratory data presented in this manuscript.