
Being an important cause of death, but also disability, ischemic stroke has an increasing incidence in young adults (1). Most patients have residual neurological deficits six months after the event (2). Data show that almost 35% of ischemic strokes could be cryptogenic, meaning the etiology remains unknown despite careful assessment (at least arterial imaging, echocardiography, rhythm monitoring, and relevant laboratory testing, such as lipid profile and hemoglobin A1c) (3). It is also important to evaluate thyroid function, as hypothyroidism seems to be an independent risk factor for neurological events (4). On the other hand, data suggest that in acute ischemic stroke, significant derangement in thyroid hormones occurs (hypothalamo-pituitary-thyroid axis damage), with some encouraging the use of low T3 levels as an indicator of poor prognosis (5). Previous studies have reported that women tend to experience stroke at an older age than men. Furthermore, obesity, active smoking, and the presence of the C allele of the angiotensin II type 1 receptor gene have been associated with an increased risk of stroke in women, highlighting the contribution of both genetic and environmental factors to cerebrovascular disease (6). Among cryptogenic strokes, a subset of patients with embolic stroke of undetermined source (ESUS) was described (Table 1) (7).
| Non-lacunar stroke on CT or MRI (Lacunar stroke being defined as a subcortical infarct ≤1.5 cm (≤2 cm on MRI diffusion images) in the distribution of the small, penetrating cerebral arteries) |
| Absence of extracranial or intracranial atherosclerosis causing ≥50% luminal stenosis in arteries supplying the area of ischaemia |
No major-risk cardioembolic source of embolism
|
No other cause of stroke identified
|
Patent foramen ovale (PFO) is defined as the persistence into adulthood of a normal embryological communication between the two atria (8). About 25% of adults have PFO (9). It appears to be involved in 50% of cryptogenic strokes (10) and 10% of all strokes in young adults (18-60 years) (11).
Due to the high prevalence of both PFO and cryptogenic stroke, including ESUS, it is very hard to prove an actual link between them. It is generally accepted that PFO can lead to stroke through paradoxical embolism, and increases in right-to-left shunting (Valsalva maneuver) amplify the risk. Also, another possible mechanism is represented by in situ thrombus formation (within the PFO or atrial septal aneurysm) (9).
The reported rate of recurrent stroke after cryptogenic stroke associated with PFO appears to be higher in older patients than in younger patients, suggesting other possible causes in addition to paradoxical embolism (11).
To evaluate the likelihood of PFO being the cause of stroke, there are two risk scores clinicians use in everyday practice. The RoPE (Risk of Paradoxical Embolism) score includes clinical and paraclinical data, but also behavioral features and age (12). PFO-Associated Stroke Causal Likelihood (PASCAL) classification includes the RoPE score and anatomical features of PFO (13). A high RoPE score ( ⩾ 7) suggests a higher probability that the detected PFO is causally related to the index stroke rather than being an incidental finding. Furthermore, by integrating the RoPE score into the PASCAL classification system, we can establish the possibility/probability of stroke being related to PFO (14). Those two scores are also used in patient selection for PFO closure, but we must mention that several limitations have been pointed out. RoPE score does not prove causality, but probability (15). It also ignores PFO anatomic features; it is derived from retrospective data; and it has limited utility in older patients, who often receive low scores due to the presence of other vascular risk factors, so the score may underestimate the role of PFO in those cases. On the other hand, PASCAL classification does not prove causality either, but classifies the likelihood of PFO-related stroke. In addition, it demands detailed ultrasonography, and the results could be altered by the technique or operator experience (16).
Secondary prevention options after a PFO-associated stroke consist of antiplatelet therapy, anticoagulant therapy, or percutaneous closure of PFO (17). It is still debatable which option is better, with some studies showing superiority of PFO closure compared to antiplatelet and anticoagulant therapy, while others claim no difference in outcome or inconclusive evidence for either of them (18).
The aim of this focused review is to critically summarize current evidence comparing PFO closure with medical therapy for secondary prevention after PFO-associated cryptogenic stroke, with particular emphasis on patient selection and medium- and long-term outcomes. Also, several studies have reported an association between elevated cardiac biomarkers and increased stroke severity: higher CK-MB concentrations during the acute phase of ischemic stroke have been observed in patients with more severe neurological deficits, indicating that myocardial involvement may accompany extensive cerebrovascular injury (19).
A structured literature search was conducted in PubMed/MEDLINE for articles published between 01 January 2010 and 31 December 2025. We searched PubMed database for suitable literature data on the comparison of PFO closure with medical therapy for secondary prevention of recurrent cerebrovascular events in patients with PFO-associated cryptogenic stroke using PubMed MeSH terms, such as (“Patent Foramen Ovale”[Mesh] OR “patent foramen ovale”[tiab] OR PFO[tiab]) AND (“Stroke”[Mesh] OR “Ischemic Stroke”[Mesh] OR “ischemic stroke”[tiab] OR “cerebral infarction”[tiab] OR TIA[tiab]) AND (“Heart Septal Defects, Atrial/surgery”[Mesh] OR closure[tiab] OR occlusion[tiab] OR “device closure”[tiab] OR “transcatheter closure”[tiab]) AND (“Recurrence”[Mesh] OR recurrence[tiab] OR recurrent[tiab] OR “stroke recurrence”[tiab]). Regarding the inclusion criteria, we selected records of patients with PFO and a history of stroke, and we filtered our results by study design (clinical studies, clinical trials, multicenter studies, observational studies, randomized controlled studies) and date of publication. Also, we chose to include only free full-text sources. On the other hand, according to our exclusion criteria, studies of children, studies comparing different devices or techniques, and observational studies that focused on long-term complications and recurrence predictors were excluded from the review. The selected studies were narratively synthesized, with emphasis on study design, population characteristics, therapeutic strategies, recurrent stroke outcomes, and follow-up duration. The findings were interpreted qualitatively, with particular attention to differences in patient selection and medical treatment across trials.
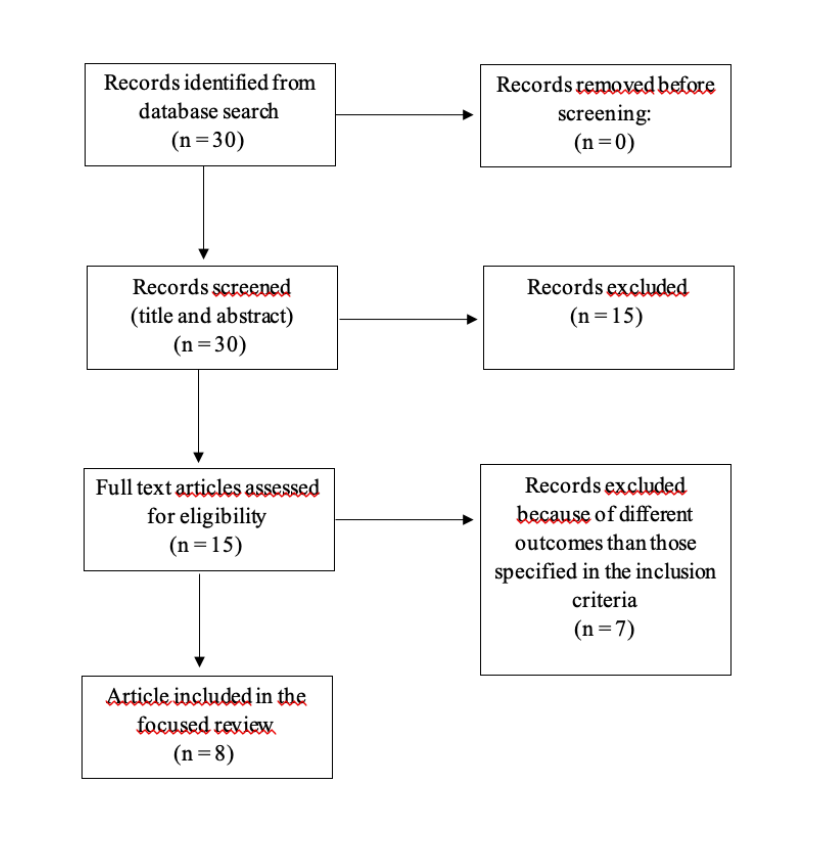
We identified 30 records from the PubMed database search. No record was removed before screening. Half of the studies (n = 15) were excluded after screening by title and abstract. After that, a full-text article assessment led to the exclusion of another 7 studies due to outcomes that differed from those specified in the inclusion criteria. Finally, 8 records were included in the review process. The selection process is also illustrated through the following diagram (Figure 1).
In the end, selected studies were compiled in an Excel spreadsheet, from which we extracted data on authors, study acronym, study type, year of publication, number of participants, randomization rate, primary endpoint, and comparison in the discussion and conclusions. We chose to include those studies that compared PFO closure and antiplatelet therapy to medical therapy alone (antiplatelet therapy/anticoagulation). We reviewed eight records, involving 3750 participants, all of whom were diagnosed with PFO and stroke, designed to compare different therapeutic strategies to prevent stroke recurrence (PFO closure vs medical therapy alone).
CLOSURE I (21) was a multicenter, randomized, open-label trial published in 2012 and one of the earliest reports on the subject. It included 909 patients, randomly assigned in equal proportions to two groups: one group underwent PFO closure in addition to antiplatelet therapy, and the other received medical therapy alone (warfarin, aspirin, or both). Primary endpoints were stroke recurrence, transient ischemic attack, and death. In the end, this trial found no significant difference between the two management strategies in terms of stroke recurrence. PC TRIAL (22), also a multicenter, randomized, open-label trial, published one year later, in 2013, included 414 patient, with a randomization ratio of 1:1, distributed in two arms: patients who had PFO closure as wall as antiplatelet therapy (aspirin/ticlopidine/clopidogrel) and patients who reciened medical therapy only (antiplatelet therapy alone or oral anticoagulation alone – left to the discretion of the treating physician). Primary endpoints consisted of death, nonfatal strokes, transient ischemic strokes, and peripheral embolism. The results showed no significant difference between the two treatment options. The RESPECT (23) trial was a multicenter, randomized, open-label trial published in 2013, enrolling 980 patients randomized in a 1:1 ratio into two groups: those who underwent PFO closure in addition to antiplatelet therapy and those who received medical therapy exclusively (aspirin, clopidogrel, warfarin, or aspirin plus extended-release dipyridamole). It was one of the first major trials to suggest significantly lower stroke recurrence with PFO closure. Primary endpoints were stroke recurrence and death. This trial had a follow-up in 2017 (24), and the results were consistent with the initial findings. The CLOSE trial (25), another randomized, multicenter, open-label trial published in 2017, included 663 patients randomized by a 1:1:1 ratio in three groups: patients who had PFO closure besides antiplatelet therapy, patients who were given antiplatelet therapy alone (clopidogrel, aspirin, or aspirin combined with extended-release dipyridamole), and patients who received oral anticoagulation exclusively (vitamin K antagonists or direct oral anticoagulants). Its primary endpoint was stroke recurrence. The findings illustrated a significantly lower rate of stroke recurrence with PFO closure. Otherwise, the effects of oral anticoagulant therapy as compared with antiplatelet therapy on the risk of stroke recurrence could not be determined. The Gore REDUCE trial (26), also a multicenter, randomized, open-label trial published in 2017, included 664 patients randomized in two arms by a 2:1 ratio: patients with PFO closure along with antiplatelet therapy and patients who took antiplatelet therapy solely (aspirin, aspirin combined with extended-release dipyridamole, or clopidogrel). Primary endpoints included stroke recurrence, transient ischemic attack, and death. Final data illustrated significantly lower rates of stroke recurrence with PFO closure. This study had a follow-up in 2021 (27), and the results were consistent with the initial findings. The DEFENSE-PFO trial (28), a randomized, open-label, multicenter trial published in 2018, including 120 patients randomized by a 1:1 ratio in two groups, one with patients who had PFO closure plus antiplatelet therapy and one with patients who received medical therapy alone (aspirin, aspirin and clopidogrel, aspirin and cilostazol or warfarin), showed significantly lower rates of stroke recurrence with closure of the PFO in combination with medical therapy than with medical therapy alone. Its primary endpoints were stroke recurrence, death, and major bleeding (Table 2).
| No. | Study | Type of study | Year | Number of participants | Primary endpoint | Comparison in study | Conclusions |
|---|---|---|---|---|---|---|---|
| 1 | CLOSURE I | Multicenter, randomized, open-label trial | 2012 | 909 (1:1) | Stroke, death | PFO closure (as soon as possible, preferably 7days) plus antiplatelet therapy vs medical therapy alone (warfarin, aspirin or both) | No significant difference |
| 2 | PC Trial | Multicenter, randomized, open-label clinical trial | 2013 | 414 (1:1) | Death, nonfatal stroke, transient ischemic attack, peripheral embolism | PFO closure (as soon as possible) plus antiplatelet therapy (aspirin/ticlopidine/clopidogrel) vs medical therapy alone (antiplatelet therapy alone or oral anticoagulation alone – left to the discretion of the treating physician) | No significant difference |
| 3 | RESPECT | Multicenter, randomized, open-label trial | 2013 | 980 (1:1) | Stroke, death | PFO closure (within 21 days) plus antiplatelet therapy vs medical therapy alone (aspirin, warfarin, clopidogrel or aspirin combined with extended-release dipyridamole) | Recurrent ischemic stroke was significantly lower with PFO closure plus antiplatelet therapy than with antiplatelet therapy alone. |
| 4 | RESPECT follow up | 2017 | |||||
| 5 | CLOSE | Multicenter, randomized, open-label trial | 2017 | 663 (1:1:1) | Stroke | PFO closure (within 21 days) plus antiplatelet therapy vs antiplatelet therapy alone (aspirin, clopidogrel, or aspirin combined with extended-release dipyridamole) vs oral anticoagulation alone (vitamin K antagonists or direct oral anticoagulants) | Recurrent ischemic stroke was significantly lower with PFO closure plus antiplatelet therapy than with antiplatelet therapy alone. The effects of oral anticoagulant therapy as compared with antiplatelet therapy on the risk of stroke recurrence could not be determined. |
| 6 | Gore REDUCE | Multicenter, randomize, open-label trial | 2017 | 664 (2:1) | Stroke, transient ischemic attack, death | PFO closure (within 90 days – median of 28 days) plus antiplatelet therapy vs antiplatelet therapy alone (aspirin, aspirin combined with extended-release dipyridamole or clopidogrel) | Recurrent ischemic stroke was significantly lower with PFO closure plus antiplatelet therapy than with antiplatelet therapy alone. |
| 7 | Gore REDUCE follow up | 2021 | |||||
| 8 | DEFENSE-PFO | Multicenter, randomized, open-label trial | 2018 | 120 (1:1) | Stroke, death, major bleeding | PFO closure (as soon as possible) plus antiplatelet therapy vs medical therapy alone (aspirin, aspirin combined with clopidogrel, aspirin combined with cilostazol or warfarin) | Recurrent ischemic stroke was significantly lower with closure of the PFO in combination with medical therapy than with medical therapy alone |
We reviewed eight records, six of them being multicenter randomized open-label trials and two of them being follow-ups. The findings demonstrated a relative benefit from PFO closure in terms of stroke recurrence. Two out of eight records (25%) indicated no significant difference when comparing PFO closure and antiplatelet therapy to medical therapy alone (antiplatelet therapy/anticoagulation), while the rest of them (six out of eight, 75%) indicated superiority of PFO closure and antiplatelet therapy in stroke recurrence. We also noticed that the two studies demonstrating similar therapeutic efficacy were among the earliest large trials on this topic, while more recent studies suggest a definite benefit of PFO closure on stroke recurrence. Future research could focus on better scores to determine the causality of PFO in cryptogenic stroke, optimal therapeutic options, optimal medical therapy alone, and best imaging techniques (contrast-enhanced transthoracic echocardiogram, contrast-enhanced transoesophageal echocardiogram, contrast-enhanced transcranial Doppler).
An additional challenge in interpreting the available trials is the heterogeneity of medical therapy used in the control groups. “Medical therapy” encompassed antiplatelet agents, oral anticoagulation, or combinations of different agents, and treatment allocation was sometimes left to the discretion of the treating physician. Consequently, the available evidence more robustly addresses the question of PFO closure versus heterogeneous medical management than the specific comparative efficacy of closure versus antiplatelet therapy or anticoagulation individually. The optimal medical strategy for patients who do not undergo closure therefore remains less clearly defined.
Taken together, current evidence suggests that the clinical question has shifted from whether PFO closure is generally effective to identifying which patients are most likely to derive a net benefit from the procedure. The available randomized evidence supports closure in appropriately selected patients with PFO-associated cryptogenic stroke, particularly when alternative stroke mechanisms have been carefully excluded and clinical and anatomical features increase the likelihood of PFO causality.
This focused review had several limitations. First, the available randomized evidence is based on a relatively small number of trials, with few recent large-scale randomized studies, none of which have been published. There were only two follow-up studies, so it is difficult to appreciate accurate long-term efficacy and prognosis. Furthermore, in PFO closure groups, different devices were used, and at the same time, in medication-alone groups, the choice between antiplatelet therapy and anticoagulation, as well as which specific drug was used, varied between trials, making it hard to draw a reliable conclusion.
Age represents another unresolved issue in the explored domain. Most randomized trials supporting PFO closure predominantly enrolled younger patients, whereas evidence in individuals older than 60 years remains substantially more limited. In older patients, competing mechanisms of stroke—including occult atrial fibrillation and atherosclerotic disease—become increasingly prevalent, while the RoPE score tends to assign a lower probability of PFO causality because of age and accompanying vascular risk factors. Whether carefully selected older patients with high-risk PFO anatomy may nevertheless benefit from closure remains an important area for future investigation.
This focused review aimed to compare different therapeutic strategies to prevent stroke recurrence (PFO closure vs medical therapy alone). Current evidence supports PFO closure as an effective strategy for reducing recurrent stroke in appropriately selected patients with PFO-associated cryptogenic stroke. However, treatment decisions should incorporate clinical characteristics, PFO anatomy, the likelihood of a causal relationship between the PFO and the index event, competing stroke mechanisms, and the risks associated with both interventional and medical strategies. Also, we would like to point out the need for further research, considering that the latest large-scale study on this subject was published in 2018 and that access to diagnostic investigations and closure procedures has improved in recent years. It is expected that more data on this topic would optimize patient selection and evaluation of medium- and long-term prognosis.
The authors declare no conflict of interest. This research received no external funding.
No generative AI was used in the production of this article.
Conceptualization, I.G., A.B.,F.A.A., and C.A.S.; methodology, I.G., A.B., F.A.A., and A.A.B.; software, A.A.B.; validation, A.A.B. and C.A.S.; formal analysis, I.G., F.C.P., and A.A.B.; investigation, I.G. and A.B.; resources, C.A.S., and F.C.P.; data curation, I.G. and A.B.; writing—original draft preparation, I.G. and A.B.; writing—review and editing, A.A.B. and C.A.S.; visualization, I.G. and A.A.B.; supervision, C.A.S., and F.C.P. ; project administration, A.A.B., F.A.A., and C.A.S. All authors have read and agreed to the published version of the manuscript.
Not applicable.
Not applicable.